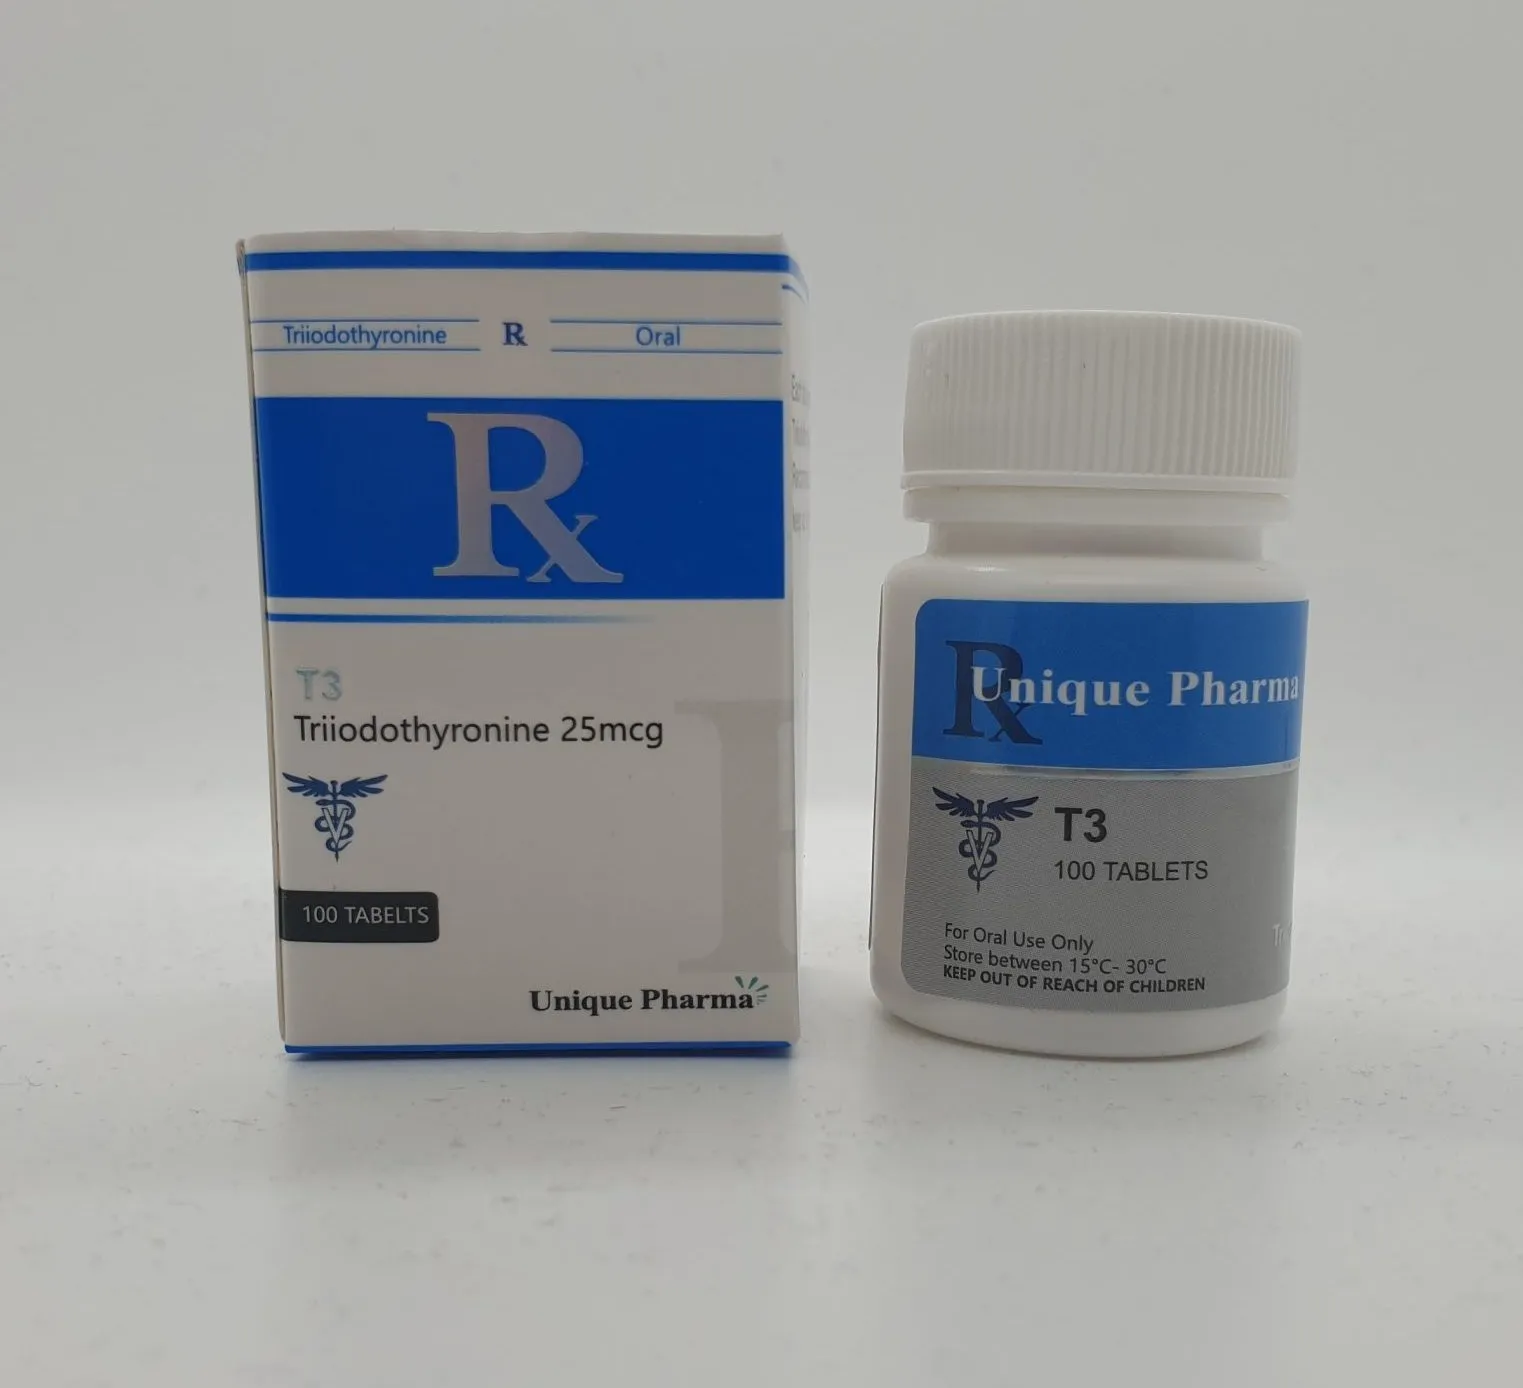
Unlock Rapid Fat Loss
T3 (Liothyronine Sodium) is one of the most potent metabolic enhancers available for bodybuilders and athletes. Unlike standard fat burners, T3 is a synthetic form of the thyroid hormone triiodothyronine, which directly regulates your body's metabolic rate.
By increasing the amount of T3 in your system, you essentially force your body to burn calories at an accelerated rate, even at rest. This makes it an invaluable tool for cutting cycles, contest prep, or breaking through stubborn weight loss plateaus.
Key Benefits:
- Extreme Fat Loss: Drastically increases basal metabolic rate (BMR).
- Preserve Muscle: When stacked with anabolic steroids, it helps strip fat without destroying lean tissue.
- Enhanced Energy: Boosts nutrient turnover and energy utilization.
- Rapid Results: Visible changes in body composition in weeks.
Dosage & Administration:
T3 is powerful and must be respected. A typical cycle starts low (e.g., 25mcg per day) and gradually tapers up to a maximum (usually 75-100mcg), then strictly tapers back down to allow natural thyroid function to recover. Cycles typically last 6-8 weeks.
Stacking:
For the ultimate cutting physique, T3 is often stacked with Clenbuterol and anabolic steroids like Winstrol, Trenbolone, or Testosterone Propionate to prevent muscle catabolism while shredding fat.
Why Choose Unique Pharma T3?
We supply only legitimate, lab-tested T3. Dosage accuracy is critical with thyroid hormones, and our products are verified for concentration and purity.
Chemical Profile
- Generic name: Liothyronine Sodium (commonly known as T3)
- Chemical class: Synthetic thyroid hormone
- Molecular formula: C15H11I3NNaO4
- Molecular weight: approximately 672.96 g·mol−1
- Physical form: oral solid dosage (tablets)
- Terminal elimination half-life: approximately 2.5 days
Clinical Pharmacology
T3 (Liothyronine) is the active form of thyroid hormone that directly affects cellular metabolism. It increases basal metabolic rate, enhances protein synthesis, and promotes lipolysis. Unlike T4, T3 does not require conversion and acts directly on thyroid hormone receptors.
Applications
- Enhancement of metabolic rate during cutting phases
- Fat loss acceleration
- Maintenance of metabolic function during caloric restriction
- Synergistic use with anabolic compounds
Dosage Guidelines
Typical dosing starts at 25mcg daily and may be gradually increased. Maximum recommended doses vary but typically do not exceed 75-100mcg daily. Tapering protocols are essential to prevent thyroid suppression. Always consult with a healthcare professional before use.
1. Description: Clinical summary
"T3" refers to triiodothyronine (active thyroid hormone, chemical abbreviation T3). Clinically, liothyronine sodium is the pharmaceutical preparation of T3 used to treat certain thyroid-related disorders. T3 is the metabolically active thyroid hormone that increases basal metabolic rate, potentiates catecholamine effects, and regulates development and differentiation in many tissues.
Primary clinical uses
- Replacement or adjunctive therapy in hypothyroidism (less commonly used as sole long‑term replacement than levothyroxine/T4).
- Short‑term use when more rapid onset of action is desired.
- Treatment of severe, life‑threatening hypothyroidism (myxedema coma) as part of emergency management (often IV).
- Diagnostic uses historically (suppression/stimulation tests) but rarely used for this today.
General considerations
- T3 has a faster onset and shorter half‑life than T4 (levothyroxine). Because of this, it causes more rapid changes in serum thyroid hormone levels and clinical effect but also more fluctuation and higher risk of iatrogenic thyrotoxicosis if not carefully dosed.
- T4 (levothyroxine) is preferred for most chronic replacement because it is converted to T3 peripherally and provides steady levels. T3 may be used in selected patients (e.g., persistent symptoms despite normalized TSH on T4, need for rapid correction, or specific endocrinologist-directed combination therapy).
2. How does t3 work?: Mechanism of action
- T3 binds to nuclear thyroid hormone receptors (TRα and TRβ) in target tissues. The hormone‑receptor complex modulates transcription of thyroid‑responsive genes, affecting protein synthesis and metabolic activity.
- Effects at the cellular level include increased mitochondrial activity, upregulation of enzymes involved in carbohydrate and lipid metabolism, increased β‑adrenergic receptor expression (augmenting sensitivity to catecholamines), and modulation of cardiovascular function (increased heart rate and cardiac output).
- Compared with T4, T3 is the biologically active form and produces more immediate genomic and non‑genomic effects. Peripheral tissues normally convert T4 to T3 via deiodinases; pharmacologic T3 bypasses this conversion.
3. Dosage: Medical and varying usage guidelines
Important: Dosing must be individualized and supervised by a clinician. Monitor symptoms, heart rate, blood pressure and thyroid function tests (TSH; free T3/free T4 when appropriate). The following are common clinical regimens and typical ranges used in adults; institutional protocols and specialist recommendations should be followed.
Oral (liothyronine sodium)
- Typical adult replacement dosing:
- Starting dose for otherwise healthy adults: commonly 5–25 mcg once daily, titrating upward based on response and labs.
- Typical maintenance dose range: 25–75 mcg/day (often given once daily or divided into two doses to reduce peak symptoms).
- Elderly patients or those with coronary artery disease, arrhythmias, or other significant cardiac disease:
- Start very low (e.g., 5 mcg/day) and increase slowly (e.g., by 5 mcg increments every 1–3 weeks) with close cardiac monitoring.
- Combination therapy (levothyroxine + liothyronine):
- Some clinicians substitute a small dose of liothyronine for part of levothyroxine (e.g., replace a portion of T4 dose with T3 by weight-equivalence). Approximate potency conversions: 1 mcg T3 ≈ 3–4 mcg T4 — this is approximate only; any change should be made by an endocrinologist with biochemical monitoring and symptom assessment.
- Common combination regimens vary widely (e.g., 10–20 mcg T3 daily in divided doses combined with reduced T4), but approaches differ and evidence is mixed.
Intravenous (hospital, severe hypothyroidism/myxedema coma)
- IV liothyronine is used when enteral absorption is impaired or rapid correction is needed.
- Common regimens used in critical care settings (examples; follow institutional protocols):
- Loading bolus 5–10 mcg IV followed by continuous infusion of 2.5–10 mcg/hour OR
- Bolus 10–20 mcg IV followed by 1–2 mcg/hour infusion.
- Some centers use a single bolus followed by oral transition; others use different bolus sizes. Because of risk of cardiac complications, IV dosing should be performed under intensive monitoring and usually in conjunction with IV glucocorticoid administration until concomitant adrenal insufficiency is excluded.
- For myxedema coma, some guidelines recommend using levothyroxine (IV) or a combination of IV T4 + T3; local protocols vary.
Pediatric use
- Levothyroxine is the usual agent for congenital or chronic pediatric hypothyroidism. Liothyronine may be used in specific circumstances (e.g., certain testing or particular clinical scenarios) and dosing must be weight‑based and determined by pediatric endocrinology. Do not attempt to dose children with T3 without specialist input.
Off‑label and non‑medical use
- T3 has been misused for weight loss or athletic performance. This is unsafe and associated with serious cardiovascular and metabolic risks. Such use is not recommended.
Monitoring and adjustment
- When using T3, monitor heart rate and cardiac symptoms closely. Measure TSH and free thyroid hormone levels as clinically indicated. TSH may be suppressed disproportionately with exogenous T3; free T3 measurements are often useful when the drug is being used.
- Dose changes should be conservative in patients with cardiac risk, older adults, or long-standing hypothyroidism.
4. Side effects: Common and rare bad effects
Adverse effects generally reflect excess thyroid hormone (thyrotoxicosis) and are more likely if dosing is excessive or titration too rapid.
Common (dose‑related)
- Palpitations, tachycardia, increased pulse rate
- Nervousness, anxiety, irritability, tremor
- Heat intolerance, sweating
- Weight loss, increased appetite
- Insomnia
- Diarrhea, increased bowel movements
- Menstrual irregularities
- Muscle weakness
Cardiovascular and serious risks (can be life‑threatening)
- Arrhythmias (including atrial fibrillation)
- Worsening or precipitation of angina, myocardial ischemia or myocardial infarction, particularly in patients with known coronary artery disease
- Heart failure decompensation in susceptible individuals
Endocrine/metabolic
- Decreased bone mineral density and increased risk of osteoporosis (with chronic overtreatment)
- Unmasked or worsened adrenal insufficiency in patients with untreated secondary adrenal failure — adrenal status should be assessed prior to aggressive thyroid hormone replacement in some clinical contexts
Allergic/other
- Hypersensitivity reactions are uncommon but possible.
Rare but important
- Severe cardiac events (fatal arrhythmias, myocardial infarction) with inappropriate dosing or in vulnerable patients
- Acute adrenal crisis if adrenal insufficiency is unrecognized and thyroid hormone is given without glucocorticoid support in critical cases
- Severe neuropsychiatric manifestations (rare)
Drug interactions that increase adverse effects
- Concomitant sympathomimetics or catecholamines may potentiate cardiac effects.
- Warfarin anticoagulation may be potentiated (increased INR) as thyroid hormone increases catabolism of vitamin K‑dependent clotting factors; monitor INR and adjust anticoagulant dose.
- Drugs that alter absorption (e.g., bile acid sequestrants, calcium/iron supplements, proton pump inhibitors) or metabolism (amiodarone, propylthiouracil, beta‑blockers, certain enzyme inducers/inhibitors) may affect T3 levels or response.
If any signs of cardiac ischemia, new arrhythmia, severe tremor, or other severe symptoms occur, stop the drug and seek urgent medical care.
5. Storage: HOW to store it
- Keep the medication in its original container with label intact.
- Store at controlled room temperature, typically 15–30 °C (59–86 °F), unless the product labeling specifies otherwise.
- Protect from moisture and light; keep the container tightly closed.
- Keep out of reach of children and pets.
- Do not use past the expiration date printed on the packaging.
- For liquid formulations or hospital IV preparations, follow manufacturer or institutional pharmacy guidance about storage, dilution, and stability (e.g., discard opened vials per policy).
- Dispose of unused medication safely per local regulations or pharmacy take‑back programs.
Additional practical and safety notes
- Do not self‑adjust dose: changes should be guided by a clinician and laboratory monitoring.
- Before initiating T3 (especially at higher doses or IV), evaluate cardiac status and consider ECG monitoring in older patients or those with cardiac disease.
- In pregnancy, levothyroxine (T4) is generally preferred for replacement; if T3 is used, do so under specialist supervision with close monitoring.
- Keep a list of all medications and supplements and inform your clinician, since timing of doses relative to calcium, iron, or antacids affects absorption.
Summary
Liothyronine (T3) is the active thyroid hormone used medically for selected indications where rapid onset or specific effects are desired. It requires careful dosing, monitoring, and consideration of cardiovascular risk. Use should be guided by an endocrinologist or treating physician; inappropriate dosing or non‑medical use can cause serious harm.